


Corporate Wellbeing Strategy: How Leaders Prevent Burnout and Build Workforce Resilience
March brings together an unexpected convergence of global health conversations. World Kidney Day highlights disease prevention. Nutrition campaigns promote healthier habits. Millions observe Ramadan, reflecting on discipline and balance.
On the surface, these seem unrelated to your priorities as an HR leader. But look closer, and they reveal something your organisation can’t afford to ignore.
The Hidden Crisis Affecting Your Workforce Right Now
Across the global workforce, chronic health conditions are rising faster than most leaders realise. Kidney disease affects 850 million people worldwide—many undiagnosed until it’s too late. Cardiovascular disease claims nearly 18 million lives annually. Diabetes, obesity and burnout continue their upward trajectory.
These aren’t just healthcare statistics. They’re productivity indicators sitting in your quarterly reports.
Because here’s what the data shows: declining employee health directly undermines cognitive performance, decision-making quality, stress regulation and sustained energy. The people you’re counting on to navigate complexity and drive results are increasingly operating below their capacity.
The Concept Smart Organisations Are Acting On
Public health researchers have a term that’s becoming essential for workforce strategy: compression of morbidity.
The principle is straightforward. Rather than spending decades managing chronic illness, people who maintain healthier lifestyles delay disease onset and compress illness into a shorter period near life’s end. They remain vital, capable and engaged for longer.
For your organisation, this translates to a workforce that thinks more clearly, adapts more effectively and sustains performance over time—not one that gradually declines.
Traditional Health vs Compression of Morbidity
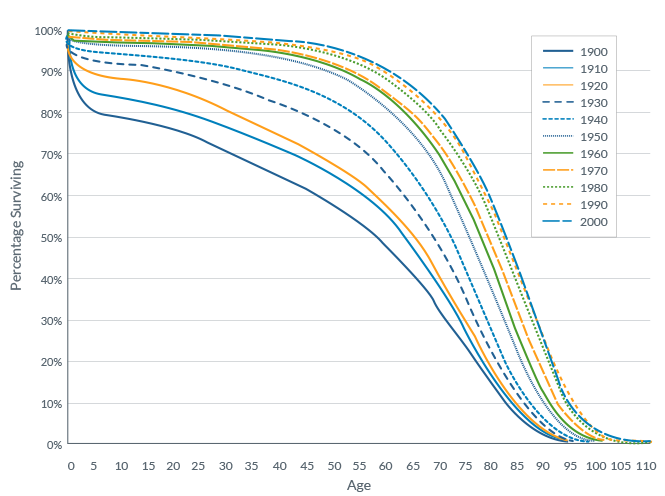
The difference? Years of sustained high performance versus gradual capability erosion.
Why This Matters to Your Bottom Line
Consider the kidneys—quietly filtering 180 litres of blood daily, regulating blood pressure, balancing fluids, removing toxins. One of the body’s most demanding systems, yet largely invisible until something goes wrong.
Modern workplace patterns are placing extraordinary strain on this system. High-sodium cafeteria food. Insufficient hydration. Sedentary desk work. Unmanaged chronic stress. The result? One in ten adults now lives with chronic kidney disease.
Your workplace environment directly influences these outcomes. The question is whether it’s influencing them positively or negatively.
March’s health observances offer practical insight. During Ramadan, millions practice intentional eating patterns that encourage metabolic reset and self-discipline. The principles behind safe fasting—proper hydration, balanced whole-food nutrition, body awareness—mirror the fundamentals of sustainable performance.
This isn’t about implementing fasting programmes. It’s about recognising that intentional approaches to nutrition, recovery and energy management create measurable performance advantages.
From Early Career to Late Career: The Lifecycle Challenge
Research shows that dietary and lifestyle habits established in early adulthood determine disease risk decades later. Yet most organisations treat employee health as static, offering one-size-fits-all wellness programmes that miss the mark.
The reality is more nuanced:
- 20s-30s: Building foundations through balanced nutrition, movement and sleep
- 40s-50s: Managing metabolic health, cholesterol and blood pressure
- 60s+: Maintaining muscle strength, bone density and cognitive vitality
Across every stage, the pattern remains consistent: whole foods, lean proteins, healthy fats and regular movement support cardiovascular health, reduce inflammation and maintain stable energy.
For HR leaders, this creates both a challenge and an opportunity. How do you design interventions that meet people where they are across different life stages and career phases?
Why Traditional Wellness Programmes Keep Failing
Most wellness initiatives treat wellbeing as optional—a perk, not a performance driver. They offer gym memberships employees don’t use, lunch-and-learn sessions quickly forgotten, annual health checks that don’t translate to behaviour change.
The organisations we work with understand something different: resilience and wellbeing are strategic capabilities, not nice-to-have benefits.
When your people have the physical and mental capacity to navigate pressure without burning out, everything else improves. Decision quality. Team dynamics. Innovation. Retention. Client relationships.
The most sustainable organisations are built on sustainable people. It’s that simple.
A Different Approach to Workforce Sustainability
At The Resilience Institute, we partner with HR leaders who recognise this shift. Our programmes translate resilience science into practical workplace habits that support sustainable high performance.
Our Well-Being Journey combines diagnostic insights with targeted microlearning to strengthen:
- Energy management across demanding schedules
- Burnout prevention and early warning recognition
- Mental fitness and cognitive performance
- Practical recovery strategies
Organisations often pair this foundation with targeted leadership development:
- High-Performance Leadership – Equipping leaders to sustain their own performance while modeling healthy cultures
- Resilience in Change and Challenge – Building adaptive capacity when pressure intensifies
- Interpersonal Resilience – Strengthening team dynamics and psychological safety
Each programme is tailored to your organisation’s specific context, challenges and goals. We deliver through workshops, coaching dialogues, microlearning journeys or keynote sessions—whatever matches your workforce needs.
The Question Isn’t Whether, It’s How
You already know wellbeing matters. The real question is: how do you design an environment where people perform at their best without compromising their long-term health?
March offers a timely reminder that the decisions you make about workforce health today will determine your organisational capacity five, ten, fifteen years from now.
The choice is between gradual capability decline and sustained high performance. Between reactive healthcare costs and proactive capability building. Between treating people as resources to extract from and humans to invest in.
Let’s Talk About What’s Possible
If you’re exploring how to strengthen resilience, wellbeing and sustainable performance across your teams, we’d welcome the conversation.
Contact us to discuss a tailored programme for your organisation →
Because the most competitive advantage you can build in 2026 isn’t another technology platform or process optimisation. It’s a workforce that stays healthy, engaged and high-performing for the long term.
You can explore our programmes or enquire here:
https://resiliencei.com.sg
Original Source: https://resiliencei.com.sg/corporate-wellbeing-strategy-workforce-resilience/
Frequently Asked Questions (FAQs)
Compression of morbidity refers to delaying the onset of chronic disease so that people remain healthier for longer and experience shorter periods of illness later in life.
Healthy employees maintain higher cognitive performance, adapt better to stress and sustain productivity longer. Workforce health directly influences organisational resilience.
Burnout prevention strategies include leadership training, healthy work rhythms, resilience development and workplace wellbeing programmes.
Corporate resilience programmes combine leadership development, wellbeing training and behavioural science to help teams manage pressure and sustain performance.
